AI Automation for GP Clinics: Handling Repeat Script Calls
AI automation for GP clinics takes repeat script requests, checks your clinic's rules and queues them for the GP, who makes every prescribing decision.
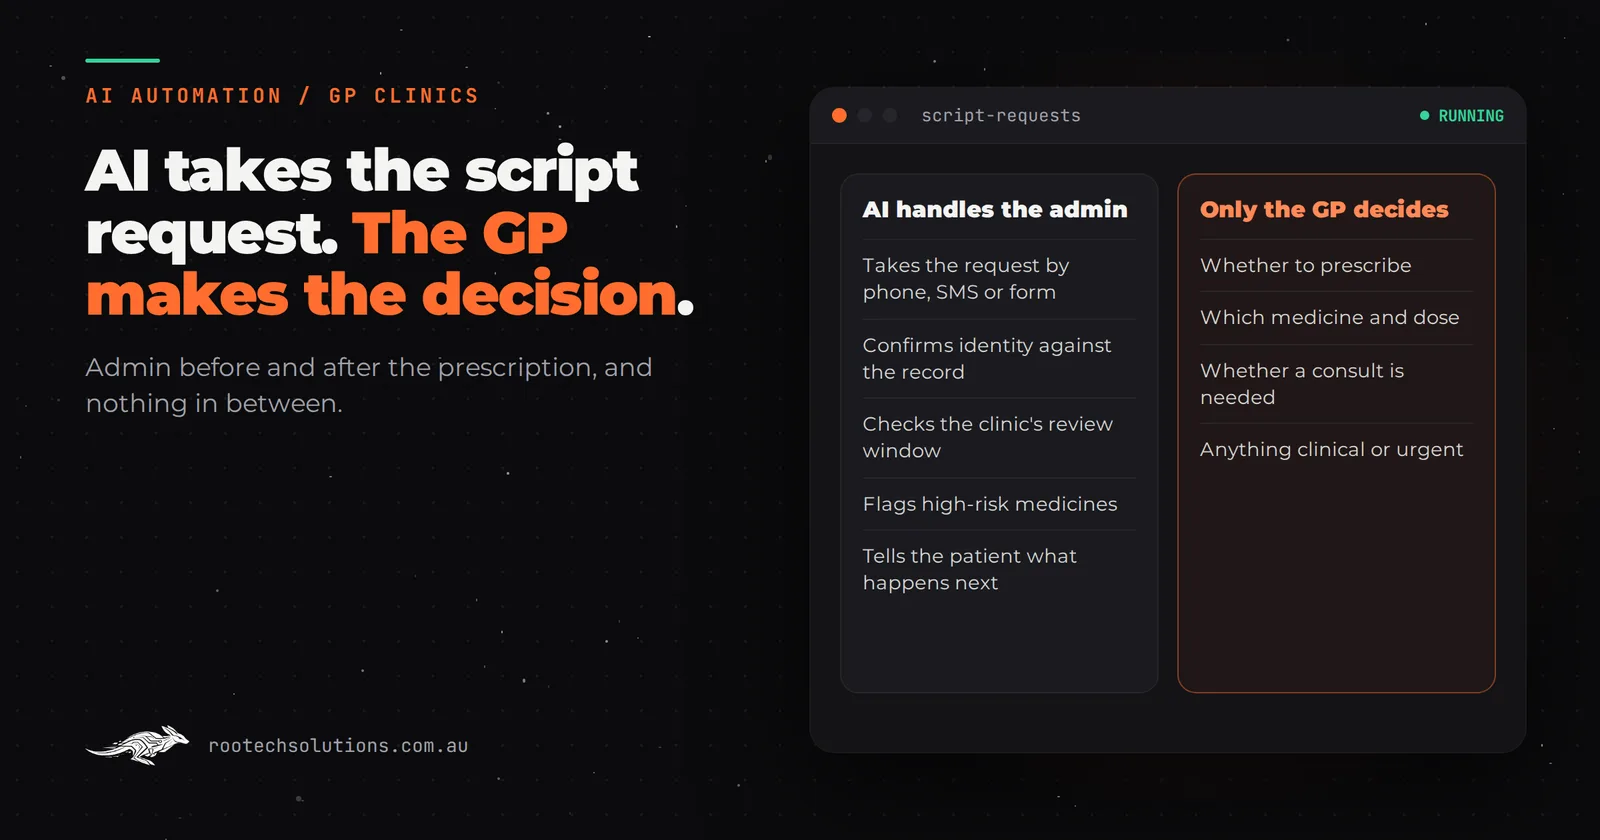
Script requests are one of the steadiest drains on a GP reception desk. The phone rings, a patient needs "my usual", and a receptionist spends several minutes taking details, checking the file, leaving a note for the doctor and promising to text when it's done, while two other lines flash. AI automation for GP clinics can take most of that admin off the desk. It can't, and must never, take any of the prescribing.
Short answer: AI can handle the admin around repeat script requests at a GP clinic: confirming who the patient is, capturing the medicine and pharmacy, checking your clinic's rules (last review date, medicines that always need a consult) and putting a tidy request in the right GP's queue. The GP decides every prescription. The AI never prescribes, approves, changes a dose or gives medical advice.
What is a "repeat script" call really asking for?
Often something different from what it sounds like. Since electronic prescriptions became common, a lot of script calls fall into three buckets, and only one of them actually needs the doctor.
- "I still have repeats but can't find the token." With an eScript, the patient gets a token by SMS or email, and for repeats the pharmacist sends a new token after each supply. Many of these callers need to check their messages, ask their pharmacy, or use an Active Script List, which keeps all their eScripts in one place. No GP time needed.
- "I've run out of repeats." This is a request for a new prescription, so it needs a doctor's decision. The admin around it can be automated; the decision cannot.
- "I need a script and I haven't been in for ages." Under most clinics' own policies, this needs an appointment first. The useful thing to do is offer one.
Sorting calls into those buckets is where a lot of the reception time goes. It's also where a well-built AI saves the most, because the first and third buckets can be resolved without anyone touching the doctor's queue.
How does AI handle a repeat script request?
It does the admin before and after the GP's decision, and nothing in between. The flow looks like this:
- Takes the request by phone, SMS or your online form, in plain language.
- Confirms identity against the patient record using the checks your clinic already uses, such as name and date of birth.
- Captures the details: medicine, strength as the patient describes it, and how they want to receive the eScript.
- Applies your clinic's rules: is the patient within the review window your doctors set, is this a medicine your doctors always want to see the patient for, and does this request belong with a particular GP?
- Routes it. Within the rules, the request goes to the right GP's queue with the record details ready to check. Outside them, the AI offers the patient an appointment from real availability.
- Closes the loop. Once the GP has made their decision in the clinical software, the patient is told what happens next, and declined requests become an offer to book.
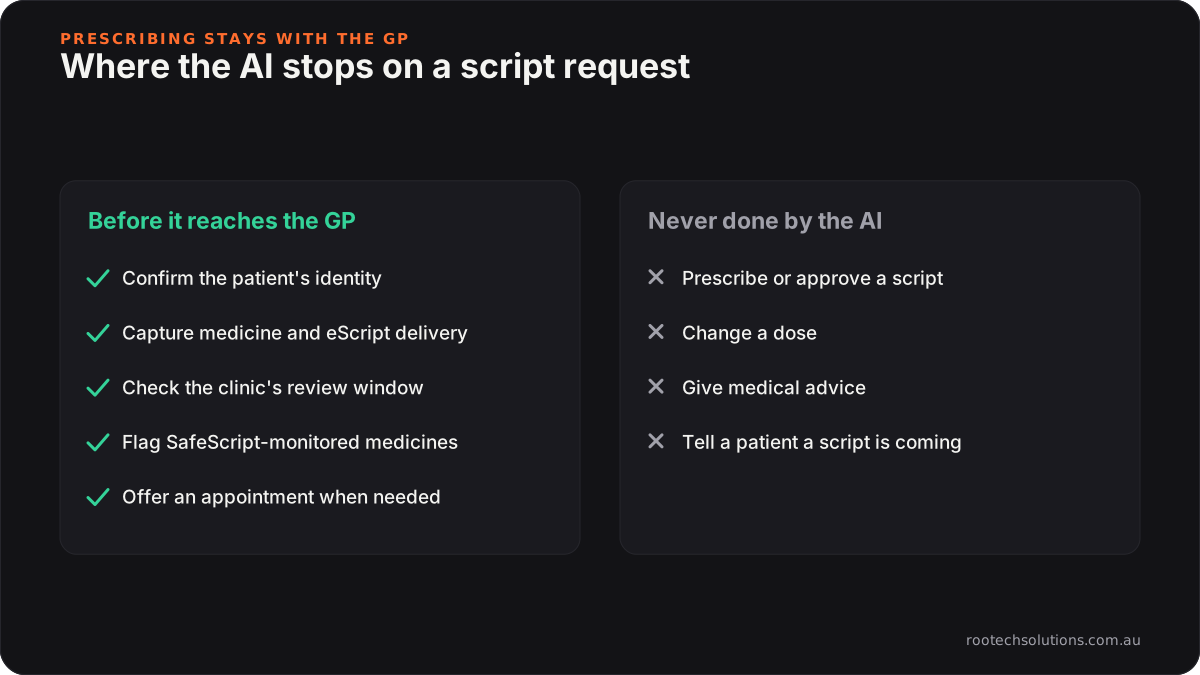
Caption: Everything on the left is admin. Everything on the right belongs to the GP.
What rules must the AI never cross?
Prescribing is a clinical decision made by a doctor, so the AI's role ends where judgement begins. Four rules should be written into any build:
- It never prescribes or approves. It never tells a patient their script "will be ready", only that the request is with the doctor.
- It flags high-risk medicines. In Victoria, it is mandatory for prescribers to check SafeScript before writing a prescription for a monitored high-risk medicine. The AI doesn't touch SafeScript; it flags requests for these medicines so the GP sees them clearly, and many clinics simply route them all to an appointment.
- It gives no medical advice. "Can I double my dose?" or "I've got new side effects" goes to a nurse or GP immediately, with the patient told someone will call.
- It escalates anything urgent. Your clinic sets the triggers, and the AI follows your instructions for directing the patient to emergency care.
Patient information is health information, so the system should also keep data in Australia, log every access, and only read the parts of the record the task needs. Ask any provider how they handle each of those before you sign.
Do clinic booking tools already handle script requests?
Some of the workflow, yes. Practice software such as Best Practice, MedicalDirector, Zedmed and Genie holds the patient record and is where the GP actually prescribes, and online booking platforms like HotDoc and HealthEngine handle appointments. If your clinic already takes script requests through an online form and staff process them comfortably, you may not need anything new. Check what your current tools offer first.
| Part of the job | Usually handled by | Where a custom AI integration helps |
|---|---|---|
| Patient record and prescribing | Clinical software (Best Practice, MedicalDirector and others) | Not involved; the GP prescribes here |
| Online appointment booking | Booking platform | Offers appointments when a request needs one |
| Taking phone script requests | Reception staff | Answers, identifies and captures the request |
| Sorting lost tokens from new scripts | Reception staff | Explains eScript repeats, routes the rest |
| Applying your doctors' rules | Reception staff, from memory | Applied the same way every time |
| Telling the patient what happens next | Reception staff, when they can | Automatic message after the GP's decision |
A custom integration earns its keep when phone requests are the bulk of the volume, when reception is the bottleneck, or when your doctors' rules are applied inconsistently because they live in people's heads. It sits beside your clinical software, not inside the prescribing.
How many script requests justify automating?
Count them before you decide. Ask reception to tally script calls and messages for one normal week, and tag each one: lost token, out of repeats, or needs an appointment. If it's a handful a day, a clear phone message and a good online form is the cheaper fix. If it's dozens a day and the phones are suffering for it, automation is worth pricing.
The time saved comes mostly from the first and third buckets disappearing from the desk, and from fewer callbacks, because the patient is told what's happening without anyone remembering to text them. If missed calls in general are the bigger problem, start with how clinics stop losing after-hours bookings instead.
What does AI automation for GP clinics cost?
A repeat script request system for a single GP clinic is typically a fixed-price build of $3,000 to $6,000, depending on how many systems it connects to, plus running costs that are often under $200 a month for a small clinic. These are estimates, not quotes, and phone-based handling costs more to run than SMS or online forms.
Most builds take two to four weeks, and they include a period where the AI runs alongside your current process with staff checking every request before anything is switched over. Your clinic provides:
- your doctors' rules: review windows, medicines that always need a consult, and which GP handles which requests;
- your script fee policy, if any, so the AI can state it accurately;
- your escalation rules for urgent or clinical messages.
We cover the patient-acceptance side, and what a broader clinic setup costs, in will patients hate AI at your GP clinic.
Frequently asked questions
Will older patients cope with an automated script line?
The phone line still works the way it always has; the patient just talks or texts their request rather than waiting on hold. Anyone who asks for a person, or who struggles with the process, should be put through to reception. A good build makes that easy, not a last resort.
Can the AI send the eScript to the pharmacy?
No. The GP issues the prescription from your clinical software, and the eScript token goes to the patient by SMS or email, who can then take or forward it to the pharmacy they choose. The AI's job is to get the request to the GP in good shape and keep the patient informed.
What if a patient's request should be declined?
The GP declines it in the normal way, and the AI tells the patient the doctor would like to see them and offers appointment times. The patient never hears a clinical reason from the AI; if they want one, a person calls them.
Does this replace our receptionists?
No. It takes the most repetitive calls off the desk so reception can look after the patients in front of them, help people who need more support, and manage the doctors' days. Most clinics use the time to answer the phone faster for everything else.
See where your reception hours go
We're a Melbourne studio that builds custom software and AI integrations for clinics and service businesses, and we take the rules in this post as seriously as you do. Book a free AI workflow audit and we'll map your script requests end to end, show what can be automated safely and what can't, and price it before you commit. The audit fee comes off your first project if you go ahead.